
• Skip to primary navigation
  • Skip to main content
  • Skip to primary sidebar
DB-I Logo

DenseBreast-info, Inc.

Get Smart About Being Dense

HOME/USA

EUROPE

Español

  • Home
  • For Patients
    • Patients Home
    • Dense Breasts: 5 Facts You Should Know
    • Is My Mammogram Enough?
    • Screening Tests After a Mammogram (Table)
    • Let’s Talk About Dense Breasts, Video Series
    • Patient Questions and Answers
    • Patient Resources by Language
    • Print: Patient Fact Sheet
    • Print: Patient Brochure
  • For Providers
    • Providers Home
    • CME/CE: “Dense Breasts, Risk, and Supplemental Screening”
    • Flow Chart: Who Needs More Screening?
    • Health Care Provider FAQs
    • Risk Model Tutorial
    • Table: Mammography Guideline Comparison
    • Table: Dense Breast Screening Guidelines
    • Table: High/Increased-Risk Screening Guidelines
    • DBI Research
    • Patient Resources
  • Screening Technologies
    • Screening Technologies Home
    • For Patients: Screening Tests After a Mammogram (Table)
    • For Providers: Cancer Detection by Screening Method (Table)
    • 2D/3D Mammography
    • Mammography AI Screening Tools, Comparative Tables
    • Breast Ultrasound (Sonogram)
    • Breast MRI
    • Contrast-Enhanced Mammography (CEM)
    • Molecular Breast Imaging
    • DBI Research
  • Inform/Insurance Laws
    • Inform/Insurance Laws Home
    • Inform: Federal FDA Dense Breast Reporting
    • Insurance
      • State Law Insurance Map and Federal HRSA Guidelines
      • State Law Insurance Table
      • Federal Insurance Bill: Find It Early Act
  • Blog & Press
  • About Us
    • About Us Home
    • Our Mission
    • World Dense Breast Day
    • Our Team
    • DBI Research
    • Let’s Talk About Dense Breasts, Video Series
    • Patient Resources
    • Contact Us
    • Please Donate
  • Our Corporate and Health Group Supporters

Blog

Could a Blood Test Offer an Additional Screening Option for Women With Dense Breasts? 

November 5, 2026 by Dense Breast Info

Background 

Dense breast tissue can obscure cancers on mammograms and is itself associated with increased breast cancer risk. Supplemental screening with MRI, contrast-enhanced mammography (CEM), or ultrasound can detect additional cancers but may involve false alarms, unnecessary procedures, higher costs, or limited access. 

Researchers are investigating blood-based tests that identify cancer-associated proteins rather than relying on breast images. One investigational approach uses automated mass spectrometry and machine learning to analyze thousands of circulating proteins for patterns associated with breast cancer. Whether such testing could improve screening remains uncertain. 

Study Description 

Horrmann and colleagues evaluated the test, developed by Astrin Biosciences, using previously collected blood samples from women with confirmed, untreated breast cancer (stages 0–IV) and healthy controls. After quality checks, 1,242 samples remained: 845 for model training and 397 for validation. Researchers used automated laboratory processing and mass spectrometry to measure approximately 7,000 proteins per sample using less than 1 milliliter of plasma. 

Separately, investigators simulated supplemental screening in 100,000 women with dense breasts to estimate potential outcomes when the blood test followed a negative mammogram. The test was not evaluated in a prospective screening population. 

Key Findings 

  • Accuracy in stored samples: The test correctly distinguished most blood samples from women with breast cancer from those of healthy controls.¹ 
  • Detection across stages and tumor types: Sensitivity was relatively high for early-stage cancers and several tumor subtypes, including invasive lobular carcinoma, although some groups contained few patients.² 
  • Cancer-associated protein signals: Researchers identified protein patterns associated with biological pathways involved in breast cancer development and progression.3 
  • Potential supplemental screening benefit: A computer simulation predicted fewer missed cancers when the blood test was added after a negative mammogram, but these benefits have not been demonstrated in clinical screening.4 

Interpretation/Implications 

The findings provide preliminary evidence that detailed blood-protein analysis can distinguish women with diagnosed breast cancer from healthy controls. This approach is of particular interest for women with dense breasts because, unlike mammography, blood-based testing does not rely on X-ray images, where dense tissue can obscure cancers. Researchers envision its potential use as a triage test following a negative mammogram, rather than as a replacement for mammography. In this proposed approach, women with negative blood test results might avoid additional MRI examinations, while those with positive results would undergo MRI to locate a suspected cancer and determine whether biopsy is needed. 

However, the study does not establish that the test can detect cancers missed by mammography or reduce unnecessary imaging in clinical practice. Breast density was not recorded, so performance specifically in women with dense breasts could not be assessed. Furthermore, a positive blood test cannot identify the location of a suspected cancer and would require additional imaging and potentially biopsy. These findings should not change current screening recommendations. 

Limitations 

This retrospective study used stored blood samples from women already known to have cancer or to be healthy, rather than women undergoing routine screening. Importantly, the findings concerning dense breasts were based entirely on simulation rather than observed clinical outcomes. A positive blood test without a corresponding imaging finding could also create uncertainty and anxiety, an issue not evaluated in this study. 

Large, independent prospective studies in diverse screening populations are necessary to determine whether the test can detect otherwise missed cancers, establish real-world false-positive rates, and assess how results could be incorporated safely into existing screening workflows. The test is marketed as a laboratory-developed test but has not received FDA clearance or approval.  

Detailed Results 

1 Overall accuracy: In the validation group, sensitivity was 92.6% (187/202; 95% CI: 88.1–95.4%), specificity was 92.3% (180/195; 95% CI: 87.7–95.3%), and the area under the curve (AUC), a measure of overall test discrimination, was 0.975 (95% CI: 0.961–0.987).

2 Detection by cancer stage and tumor subtype: Sensitivity was 85.7% (12/14) for stage 0, 88.6% (62/70) for stage I, and 96.9% (95/98) for stage II, with no statistically significant trend across stages 0–III (P=.204). By tumor subtype, sensitivity was 100% (20/20) for invasive lobular carcinoma, 94.8% (145/153) for invasive ductal carcinoma, and 90.9% (10/11) for ductal carcinoma in situ (DCIS).

3 Protein patterns: Analysis identified enrichment of cancer-associated biological pathways, including epithelial-to-mesenchymal transition and PI3K-AKT signaling.

4 Simulated screening outcomes: In a hypothetical population of 100,000 women with dense breasts, mammography alone was estimated to miss 431 cancers (95% CI: 347–521), compared with 31 (95% CI: 15–54) when universal supplemental blood testing was modeled. The combined mammography–blood test strategy was estimated to produce 16,591 false-positive results. These figures represent modeled predictions, not actual screening outcomes.
Filed Under: Blog

ACS Webinar, News from the UK, and DENSE-2 Trial

October 24, 2026 by Dense Breast Info

ACS Webinar on Breast Density and Screening

On World Dense Breast Day, DBI’s Chief Scientific Advisor, Dr. Wendie Berg participated in a provider-focused webinar hosted by the American Cancer Society (ACS) and was joined by Drs. Tracy Battaglia and Amy K. Patel.  The webinar explored how clinicians can incorporate breast density into breast cancer risk assessment and screening decisions. Discussions covered evolving evidence, supplemental screening considerations, and practical challenges such as access to care, insurance coverage, imaging resources, and implementation across different healthcare settings. The webinar recording can be viewed on YouTube and read the Q&A document for questions addressed during the session.

UK News: Breast Test Wales Empowers Women with Breast Density Information

While breast density notification is not a requirement of the UK breast screening programme, Breast Test Wales, part of Public Health Wales, will meet the growing patient interest in receiving this information and has created a process that allows women to request their breast density. Patients should contact their Breast Screening Centre directly to learn their breast density category or contact Breast Test Wales, HERE.

DENSE-2 Trial: Can Faster Supplemental Screening Reduce Missed Breast Cancers in Women with Extremely Dense Breasts?

A normal mammogram may miss cancer in women with extremely dense breasts. Following on the success of the DENSE trial of screening MRI, the Dutch DENSE-2 trial opened in November 2024 to test whether two faster supplemental screening options — contrast-enhanced mammography (CEM) and abbreviated MRI (AB-MRI) — can reduce interval cancers diagnosed between routine screenings. Researchers will also assess false alarms, safety, patient experience, and cost. Read more about why this study matters for women with dense breasts HERE.

Filed Under: Blog

Can Faster Supplemental Screening Reduce Missed Breast Cancers in Women with Extremely Dense Breasts?

October 22, 2026 by Dense Breast Info

The original Dutch DENSE trial showed that adding full-protocol breast MRI after a negative mammogram reduced interval cancers in women with extremely dense breasts. However, population-based implementation remains constrained by cost, limited scanner capacity, long acquisition times, and modest patient uptake (59% in the original trial). 

The DENSE-2 trial, launched in November 2024, is designed to show if contrast-enhanced mammography (CEM) or abbreviated MRI (AB-MRI) can significantly reduce interval cancer rates compared to standard screening mammography alone in women with extremely dense breasts and negative mammograms. In an accompanying Radiology editorial, Bahl emphasizes that supplemental screening must balance reductions in interval cancers against false-positive referrals, biopsies, patient burden, resource utilization, and cost. By evaluating AB-MRI (a ~5-minute scan) and CEM (utilizing existing mammography gantries), DENSE-2 addresses capacity constraints that preclude widespread implementation of full-protocol MRI.   

Study Description 

DENSE-2 (ClinicalTrials.gov: NCT06636370) is a multicenter randomized trial within the Dutch national screening program at 15 hospitals. The study will enroll 36,000 women aged 49–72 with extremely dense breasts and negative mammograms, randomized before consent to CEM, AB-MRI, or mammography alone (6000 to each of CEM or AB-MRI, with expected compliance of 59%, and 24,000 controls). As of April 3, 2026, 73% of target recruitment was completed. Full enrollment is expected in 2027.  

The study design aims to avoid changes in screening behavior among women assigned to usual care. For women with extremely dense breasts, DENSE-2 will assess whether supplemental imaging reduces interval cancers diagnosed between screening rounds. It is designed to compare each test with mammography alone, not directly compare CEM with AB-MRI.  

Women invited for supplemental screening can receive the same test across two biennial rounds. Trained radiologists interpret images using ACR BI-RADS lexicons for CEM and MRI. Dutch regulations prohibit BI-RADS 3 (“probably benign”) assessments.  

The primary endpoint is the first-round interval cancer rate (invasive and in situ cancers per 1,000 screens) assessed via linkage with the Dutch National Cancer Registry and is expected to report results in 2031. Secondary endpoints include incremental cancer detection rate, false-positive rate, positive predictive value, stage distribution, adverse events, participant and provider experience surveys, focus groups, and long-term health economics modeled via Microsimulation Screening Analysis (MISCAN).  

Filed Under: Blog

World Dense Breast Day Stats and Mammography Screening Tools Update

October 17, 2026 by Dense Breast Info

World Dense Breast Day Reaches 65.6 Million People

When we established World Dense Breast Day in 2021, our goal was to create a dedicated day to educate about dense breasts, implications for breast cancer screening and risk, and to provide a focal point for raising awareness globally.

With a groundswell of global involvement engaging more actively with the topic. #WorldDenseBreastDay celebrated its fifth anniversary on September 30 with extraordinary results:

  • 65.6M Reach: the total number of unique viewers of content carrying the campaign hashtag, up 22% from last year
  • 1.6M Interactions: the total number of comments, shares, likes, saves, and clicks on content with the campaign hashtag, up 2000% from last year

Thank you to every organization, clinician, advocate, and patient who posted, shared, and amplified this message around the world.

Mammography AI Screening Tools Update

Artificial intelligence in breast imaging is a fast-moving field, with new research emerging constantly. We have updated our page on AI tools used with mammography screening, adding images and expanding the comparison table with additional studies to keep the content current.  Review the updated page HERE.

Filed Under: Blog

Could Breast Tissue Stiffness Help Explain the Increased Cancer Risk in Women with Dense Breasts?

October 9, 2026 by Dense Breast Info

Women with dense breast tissue face up to a four-fold higher lifetime risk of developing breast cancer. Dense breasts feel firm because they contain a tight mesh of structural collagen proteins, stiffer tissue architecture, and an increased number of immune cells called macrophages. This structural firmness and tissue stiffness are well-known physical features of aggressive breast tumors and may be linked to treatment resistance and cancer spread.

While doctors have long recognized that dense tissue and chronic inflammation are linked to higher cancer risk, the exact physical process connecting tissue firmness to genetic DNA damage is not fully understood. Previous research has shown that macrophages can produce reactive oxygen species (ROS)  – molecules that can damage cells – but scientists did not know how stiff breast tissue might change the behavior of macrophages in a way that ultimately damages the DNA of nearby breast epithelial cells.

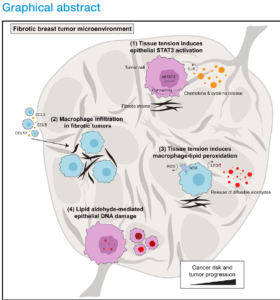
This study, led by researchers at UCSF, uncovers a clear, step-by-step chain reaction showing how physical tension in firm tissue causes breast cells to recruit immune cells (macrophages), which then produce toxic chemical byproducts that damage DNA and thereby drive tumor development.

Image source: Tissue tension fosters macrophage-driven lipid peroxidation-induced DNA damage

Study Description

This research combined human patient data, tissue samples, and specialized animal and cell models. The researchers analyzed genetic data from human breast cancer databases (TCGA-BRCA) and examined tissue samples removed during prophylactic mastectomy from women with high or low mammographic density. They also studied breast cancer in mice using various genetic modifications—including removing stress-response proteins in breast cells, deleting protective antioxidant enzymes in immune cells, and using specialized antibodies to neutralize altered fats. Advanced tools like Atomic Force Microscopy (AFM) and machine-learning mapping (STIFMap) were used to measure microscopic tissue firmness.

Key Findings

  • Stiffer breast tumors were associated with more genetic changes and mutations.¹
  • When breast tissue becomes stiff and fibrotic, it creates physical tension on surrounding cells. This mechanical pull activates a key stress-response protein inside breast cells called STAT3. Activated STAT3 causes breast cells to release chemical signals (chemokines like CCL3 and CSF1) that act like beacon flares, attracting immune defender cells called macrophages into the dense tissue.2
  • As these macrophages squeeze into the stiff environment, physical pressure forces them to produce high levels of unstable oxygen molecules (reactive oxygen species, or ROS) via an enzyme called NOX.3
  • These oxygen molecules react with fats in nearby cell membranes (a process called lipid peroxidation). This fat breakdown creates small, highly reactive chemical compounds called lipid aldehydes (such as HNE and acrolein). Unlike short-lived oxygen molecules, these toxic aldehydes easily drift into neighboring breast cells and enter the nucleus, binding to DNA and causing double-strand breaks and genetic mutations.4
  • Blocking these oxidized fats or lipid aldehydes reduced DNA damage and tumor growth in experimental models.⁵
  • Breast tissue from women with high mammographic density had more macrophages, more evidence of lipid aldehydes, and more DNA damage than tissue from women with low mammographic density.⁶

By demonstrating that tissue firmness activates a stress signal that draws in macrophages to create toxic fat byproducts, this study connects physical tissue changes directly to DNA mutations. It reveals that dense breast tissue is not just an inactive background feature, but an active player in generating genetic damage. Clinically, this discovery opens up exciting new possibilities for prevention. While it is difficult to physically soften dense tissue, these results show that we can target the chemical steps in the middle—such as using treatments that absorb toxic fat byproducts or neutralize oxidized lipids—to protect DNA and lower cancer risk in women with dense breasts.

Limitations

Much of the evidence showing how tissue stiffness leads to DNA damage came from breast cancer cells and mouse models. Although these experiments help researchers understand the individual steps involved, results from laboratory and animal models do not always translate directly to people. The study shows that dense breast tissue had more macrophages, lipid aldehydes, and DNA damage, but it cannot prove that breast density or tissue stiffness caused those changes or that women with these findings would later develop breast cancer. Larger and longer-term studies in women are needed to confirm the pathway and determine its importance in breast cancer development.

Detailed Results

¹ Analysis of human breast cancers from The Cancer Genome Atlas (TCGA) found that greater tumor fibrosis was significantly associated with higher tumor mutational burden after accounting for breast cancer subtype, TP53 mutation status, and tumor purity (P=.04). In mouse models, stiffer breast tumors also showed a broader range of genetic changes affecting protein-coding genes.

² Greater tissue stiffness increased activation of STAT3, a protein involved in cell signaling, and increased signals that attract macrophages. When STAT3 was removed from mammary epithelial cells in mice, macrophages in the surrounding tissue decreased from approximately to 20% (P<.001), and breast epithelial cells showing DNA damage decreased from approximately 34% to 18% (P<.01).

³ Macrophages grown on stiff surfaces (6 kPa) produced significantly more ROS than those grown on soft surfaces (400 Pa). In stiff mouse breast tumors, oxidation of fats within macrophages was approximately 1.5 times higher than in softer tumors (P<.001).

⁴ Exposing breast cancer cells to the lipid aldehyde 4-hydroxy-nonenal (HNE) produced increasing DNA damage with increasing exposure. L-carnosine, which can bind lipid aldehydes, reduced this damage (P<.0001). Human breast tumors with greater fibrosis also showed more evidence of mutations associated with exposure to the lipid aldehyde acrolein (P<.001).

⁵ In mice, neutralizing oxidized fats reduced the percentage of breast epithelial cells showing DNA damage from approximately 25% to 11% (P<.01) and reduced the relative area occupied by tumor from approximately 28% to 14% (P<.001). Conversely, genetically increasing lipid oxidation in macrophages increased DNA damage and lung metastases.

⁶ In prophylactic mastectomy specimens, breast tissue from women with high mammographic density had significantly more CD68+ and CD163+ macrophages than tissue from women with low density (P<.001). High-density tissue also had more epithelial cells containing HNE, a marker of lipid aldehyde exposure (P<.05), and more epithelial cells showing DNA damage (P<.001).

Filed Under: Blog

5th Annual World Dense Breast Day & Podcast Appearance by Dr. Berg

October 5, 2026 by Dense Breast Info

World Dense Breast Day

The 5th annual World Dense Breast Day brought together organizations, health care professionals, advocates, and patients from around the world for 24 hours of education about breast density and breast cancer screening. During the 24-hour blitz, DBI shared more than 100 pieces of unique content across six social media networks, resulting in over 750 posts in English and Spanish!

Thank you to the many organizations and individuals who participated, shared, posted, and helped expand the reach of this educational information. And special thanks to DBI’s Amy Pettis and Erica Maganti for their extraordinary round-the-clock support in making the event the incredible success that it was.


Podcast Series: Current Perspectives, Challenges and Possibilities with AI in Breast Imaging, Part 1

Diagnostic Imaging hosted part 1 of a podcast series on opportunities and challenges using AI in breast imaging. DBI’s Dr. Wendie Berg, Drs. Manisha Bahl and Amy Patel discussed detection benefit, reading/decision support, and risk assessment with potential to better identify women who should have screening MRI, beyond dense breasts and conventional risk factors, available HERE.

Filed Under: Blog

World Dense Breast Day is almost here!

September 26, 2026 by Dense Breast Info

#WorldDenseBreastDay Turns 5!

Officially recognized on the National Day Calendar,  #WorldDenseBreastDay is the only global awareness day devoted entirely to education about dense breasts and on September 30, we celebrate its 5th anniversary! Get ready for a 24-hour global education blitz: from midnight to midnight, new #WDBD posts will be launched, in English and Spanish, across six social media channels. Please join us and help make the 5th anniversary of #WorldDenseBreastDay our biggest educational event yet!

Follow. Share. Post (please use #WorldDenseBreastDay hashtag)

Our social media handles:

  • X: @DenseBreastInfo
  • Facebook: @DenseBreast-info, Inc.
  • Instagram: @densebreastinfo
  • Threads: @densebreastinfo
  • LinkedIn: @DenseBreast-info, Inc.
  • Pinterest: @densebreastinfo


Educational Opportunities to Support the Event:

On #WorldDenseBreastDay: To celebrate #WorldDenseBreastDay, the American Cancer Society National Breast Cancer Roundtable will launch a free provider-focused webinar exploring how clinicians can respond to breast density information to ensure optimal screening. Panel members, Dr. Wendie Berg, DBI’s Chief Scientific Advisor, and Drs. Tracy Battaglia and Amy Patel, will share practical case examples, perspectives and new resources.  When: September 30th at 12pm ET. Register HERE.

MTMI’s 2026 Breast Imaging Conference: This for-credit opportunity will focus on advancing breast imaging, improving patient care, and exploring emerging technologies shaping the future of the field and includes DBI’s Chief Scientific Advisor, Dr. Wendie Berg as a Keynote Speaker. This course is designed for mammography technologists, sonographers, radiologic technologists, and other healthcare professionals with a special interest in Breast Imaging. When: October 3rd – 4th (live or in person). Register HERE.

Filed Under: Blog

New State Insurance Bill, Corporate Supporters and More

September 18, 2026 by Erica Maganti

New State Insurance Bill

Michigan has introduced a bill to expand insurance coverage for screening and diagnostic imaging, SB1159. See our State Law Insurance Map for details on existing laws.


Corporate and Health Group Supporters

It Takes a Village!

We are grateful to our corporate supporters and donors whose generosity makes our educational outreach possible — and to the many health organizations, medical societies, and health systems that recognize the value of accurate, medically sourced information and rely on DenseBreast-info resources. From linking patients and members to our educational tools, to citing DBI resources in policy efforts, to including the DBI website link in post-mammogram communications, their support helps extend trusted breast density education far beyond our website.

Meet our “cheerleaders” HERE. And if you know of a health system or professional society using DBI resources that isn’t yet included, please let us know!


Research Roundup

Can Artificial Intelligence Locate Breast Cancer Years Before Radiologists Detect It?

Artificial intelligence (AI) may identify where breast cancers will develop years before routine screening mammography detects them. In a BreastScreen Norway study, two AI models often marked the future cancer location 2 and 4 years before diagnosis, even when radiologists considered the mammograms normal or as showing only minimal, non-specific findings. However, many examinations with high AI scores would not represent cancer, raising questions about how these signals should be used. Read more about the potential implications for earlier detection and personalized breast cancer screeningHERE.

Filed Under: Blog

Can Artificial Intelligence Locate Breast Cancer Years Before Radiologists Detect It?

September 17, 2026 by Dense Breast Info

Background

Mammographic screening helps find breast cancer early, but some cancers are difficult to recognize before they become clinically apparent. Retrospective studies have shown that 20%–30% of screen-detected and interval cancers may have signs on earlier mammograms that were not considered suspicious at the time. AI is being studied for several roles in mammographic screening, including helping radiologists detect cancer and estimating future breast cancer risk. For more information, see DenseBreast-info.org’s Mammography AI Screening Tools summary.

Some AI models assign mark potentially suspicious areas and assign a cancer likelihood score at that location. AI risk scores can be elevated years before breast cancer diagnosis, but a high score does not necessarily mean AI has identified the actual site of the future cancer.

Study Description

In this retrospective study, the authors evaluated 130,031 screening examinations from 42,371 women in BreastScreen Norway between 2008 and 2018. The study focused on women with screen-detected breast cancer who had two prior biennial screening examinations and AI risk scores in the highest 10% at both prior rounds from at least one of two AI models. Model A was the commercially available Lunit INSIGHT MMG (version 1.1.7.2) and Model B was an in-house AI model developed by the Norwegian Computing Center (NCC).

The final review included 61 cancers.1 Two experienced breast radiologists reviewed mammograms from 4 years before diagnosis, 2 years before diagnosis, and at diagnosis to determine whether AI markings matched the eventual cancer location and what mammographic findings were visible there.

Key Findings

  • AI frequently marked the future cancer location years before diagnosis. Four years before diagnosis, the two models correctly localized the future cancer in at least one mammographic view in 61% and 57% of cases. Two years before diagnosis, this increased to 81% and 75%.2
  • Even when AI correctly marked the future cancer location, radiologists classified most of the earlier mammograms as normal or showing only minimal, non-specific findings. Four years before diagnosis, 89% of cases were so classified by radiologists despite correct localization by both AI models.3
  • Mammographic features at the cancer site changed rapidly over the four years before diagnosis. Nearly three-quarters of future cancer sites had no visible mammographic findings to radiologists 4 years before diagnosis. At diagnosis, spiculated masses and asymmetry with calcifications were the most common findings.4
  • The two AI models did not identify the same cancers. Less than half of the 61 cancers were selected by both models, suggesting that different AI systems may recognize distinct mammographic and tumor features.5

These findings suggest that AI may detect subtle patterns associated with breast cancer before suspicious findings become apparent to radiologists, but this does not mean these cancers could or should have been diagnosed 2- to 4-years earlier.

At the threshold used, the authors estimated that about 93% of AI-positive examinations would not represent cancer (i.e. 7% PPV of AI-prompted recall). Automatically recalling these women would result in many false-positive examinations and unnecessary testing, and, indeed, in the absence of a finding visible to the radiologist, the cancer would likely remain undiagnosed. Instead, AI scores might eventually contribute to personalized supplemental screening, together with breast density and other risk factors, to identify women who could benefit from MRI for example. Further research is needed to determine whether acting on these signals improves patient outcomes. 

Limitations

This retrospective, single-center study included a small, highly selected sample of 61 cancers. Only cancers with high AI scores at both prior screening rounds were included [representing 61/749 (8.1%) of all breast cancers in that time period]: the findings do not apply to most screen-detected or interval cancers. Two radiologists who knew cancer was eventually diagnosed performed the retrospective review, which would influence their interpretations. The study also could not assess whether acting on early AI findings would lead to earlier diagnosis or better outcomes. Larger prospective studies are needed.

Detailed Results

1 Of 61 screen-detected cancer cases included in the study, 8 (13.1%) were DCIS (ductal carcinoma in situ) and 53 (86.9%) were invasive. Among the 53 invasive cancers, 14 (26.4%) had lymph node metastasis(es) at diagnosis. 

2 Four years before diagnosis, AI markings corresponded to the future cancer location in at least one view in 61% (26/43) of Model A cases and 57% (27/47) of Model B cases. Two years before diagnosis, this increased to 81% (35/43) and 75% (35/47), respectively. At diagnosis, the rates were 98% (42/43) and 94% (44/47).

3 Among examinations in which AI correctly marked the future cancer location 4 years before diagnosis, radiologists classified 89% (23/26) of AI-positive Model A cases and 89% (24/27) of AI-positive Model B cases as negative or having nonspecific findings. Two years before diagnosis, the corresponding proportions were 89% (31/35) and 83% (29/35).

4 Four years before diagnosis, 73% (44/61) of future cancer locations had no visible mammographic findings on radiologist review, decreasing to 47% (29/61) 2 years before diagnosis. At diagnosis, the most common findings were spiculated masses (28%, 17/61) and density with calcifications (20%, 12/61). Of the 12 cancers presenting as asymmetry with calcifications at diagnosis, 7 (58%) were evident as calcifications alone 2 years earlier.

5 Of the 61 cancers, 29 (48%) were selected by both AI models, 14 by Model A only, and 18 by Model B only. Model A-only cancers had a median invasive tumor diameter of 11 mm and included more cancers presenting as calcifications alone (29%, 4/14). Model B-only cancers had a median diameter of 15 mm and included more cancers presenting as spiculated masses (45%, 8/18).

Filed Under: Blog

ACS Roundtable, NEW Spanish Language Resources and UK Event Recap

September 11, 2026 by Dense Breast Info

#WorldDenseBreastDay Education Opportunity

To celebrate #WorldDenseBreastDay, the American Cancer Society National Breast Cancer Roundtable will launch a provider-focused webinar exploring how clinicians can respond to breast density information to ensure optimal screening. Panel members, Dr. Wendie Berg, DBI’s Chief Scientific Advisor, and Drs. Tracy Battaglia and Amy Patel, will share practical case examples, perspectives and new resources.  When: September 30th at 12pm ET. Register HERE.


Spanish Content and Forum

DBI’s Spanish-language sister site, SenosDensos.org now features patient website tools, Is My Mammogram Enough? and downloadable Guide to Ask for Additional Screening Tests in Spanish.

Forum Discussion: As part of Breast Cancer Awareness Month, Dr. Daniel Lehrer,  DBI’s MAB member and Spanish Language Advisor, will join leading researchers and organizations for The Latino Cancer Institute’s Forum #3 on social factors and breast cancer outcomes in Latinas.  When: October 2nd at 12pm ET. RegisterHERE.


UK News

Westminster Event: On 2 September, DBI’s European Education Coordinator, Cheryl Cruwys, hosted a UK Dense Breasts Drop-In event, bringing together MPs for important conversations about breast screening and patient care. The event was well attended, with strong support for greater public education and recognition of the urgent need to provide women with clear information about dense breasts, including how dense breast tissue can limit the ability of mammograms to detect cancer.

Filed Under: Blog

Can AI Help General Radiologists Perform Like Breast Imaging Specialists?

August 27, 2026 by Dense Breast Info

Background 

The accuracy of mammography depends in part on the experience and expertise of the interpreting radiologist. In the U.S.A., most screening mammograms are interpreted by general radiologists rather than fellowship-trained breast imaging specialists. Artificial intelligence (AI) may help support both generalist radiologists and specialists to improve cancer detection, as summarized in DBI’s Mammography AI Screening Tools resource. 

Recent Study 

A recent prospective multicenter study evaluated an AI-supported workflow for screening digital breast tomosynthesis (3D mammography).¹ Mammograms all had initial ProFound Pro computer-assisted detection (v. 2.x, DeepHealth) and radiologist review.  Those examinations initially considered negative by the radiologist then underwent “Safeguard Review” by AI and a preset threshold (up to 12.5% of examinations) was used to check for suspicious findings.  If there was suspicion of missed cancer on AI, the examination was routed for additional review by a breast imaging specialist, defined by formal fellowship in breast or women’s imaging (with other definitions used and results robust). Researchers compared cancer detection, recall rates, and the positive predictive value of recalls before and after implementation of the AI workflow. DeepHealth provided all financial and material support for the research. 

Key Findings 

  • The AI-supported workflow significantly increased cancer detection among general radiologists.² 
  • With AI, cancer detection by general radiologists was comparable to that of breast imaging specialists.² 
  • Cancer detection among breast imaging specialists did not significantly change with AI.³ 
  • Among general radiologists, the positive predictive value of recalls improved, though recall rates also increased.⁴ 
  • Negative mammograms in women with dense breasts were more likely to undergo AI-triggered expert review than those in women with non-dense breasts.⁵ 

These findings suggest that an AI-supported workflow can improve cancer detection by general radiologists and help narrow the performance gap between generalists and breast imaging specialists. This could be particularly useful in community settings where access to breast imaging specialists is limited. 

The findings are also of interest for women with dense breasts, since dense tissue can mask cancers on mammography. However, the study did not show that AI specifically improved cancer detection in women with dense breasts; rather, negative mammograms in women with dense breasts were more likely to undergo additional expert review. AI does not eliminate the masking effect of dense tissue or replace supplemental screening. 

The study was observational rather than randomized and did not evaluate interval cancers or false-negative rates. As Cozzi and Schiaffino note in an accompanying editorial, these gains may also come with increased downstream diagnostic workload and demands on breast imaging specialists. Further research is needed to determine whether improved screening performance translates into fewer cancers missed at screening and to better understand the impact of AI specifically in women with dense breasts. 

Detailed Results 

¹ The prospective study included 577,742 bilateral DBT screening examinations interpreted by 95 radiologists (60 generalists and 35 fellowship-trained breast imaging specialists) at 109 U.S.A. imaging facilities.  

² Among general radiologists, adjusted cancer detection increased 33%, from 3.76 cancers per 1,000 examinations (95% CI, 3.46–4.08) to 4.99 per 1,000 (95% CI, 4.51–5.53; P < .001). With AI, cancer detection did not significantly differ between generalists and specialists (P = .53). 

³ Among breast imaging specialists, adjusted cancer detection was 4.47 cancers per 1,000 examinations (95% CI, 3.94–5.07) before AI and 4.76 per 1,000 (95% CI, 4.28–5.30) with AI (P = .33). 

⁴ Among general radiologists, adjusted PPV1 (positive predictive value of recalls) increased from 3.38% to 3.89% (P = .02), while adjusted recall rate increased from 9.06% to 10.40% (P = .007). With AI, PPV1 did not significantly differ between generalists and specialists (P = .64). 

⁵ Among examinations interpreted by general radiologists, 8.96% of negative examinations in women with dense breasts underwent additional expert review compared with 6.35% in women with non-dense breasts (P < .001). Among specialists, the corresponding rates were 10.34% and 7.57%, respectively (P < .001). 

Filed Under: Blog

Reduced AI Performance in Dense Breasts

August 20, 2026 by Dense Breast Info

Larsen and colleagues examined two important issues in the implementation of AI (Transpara, v. 2.1, ScreenPoint Medical BV) in a retrospective study of 200,000 mammograms from BreastScreen Norway. The first issue was automatic breast density assessment into one of four categories: volumetric breast density (VBD) 1-4, roughly corresponding to fatty, scattered, heterogeneously dense, and extremely dense, at the breast level.  Up front, they defined 15% of examinations as VBD 1, 40% as VBD2, 40% as VBD 3, and 5% as VBD 4.  The second issue was AI breast cancer detection (based on risk score from 1-10) stratified by breast density categories; temporal comparison was not included.

Key Findings:

VBD was slightly inconsistent across vendors, though these were different mammograms.1

VBD was substantively inconsistent between breasts.2

AUC using raw AI scores decreased with increasing breast density, but a very high percentage of screen-detected cancers were given the highest risk score of 10 by the AI software.3

Interval cancer rates (which represent false negative cases on screening) increased with increasing breast density.  From 33 to 41% of mammograms in women with interval cancers diagnosed between screens had the highest AI risk score of 10, indicating they could have been detected earlier by use of AI software.

Comment:

Variability in human breast density assessment has hampered consistent application of supplemental screening guidelines and risk assessment.  Unfortunately, variability across vendors and between breasts was observed using AI to assess density: appropriately standardizing recommendations requires further refinement.  The risk score performed much better than the density score at potentially triaging mammograms to supplemental screening. While AI performed well across all breast density categories, performance was reduced in dense breasts.  Interval cancer rates could potentially be reduced by at least 33-41%, but not eliminated, by use of current AI.  This study was entirely retrospective: it is not clear that potential benefits of AI would be fully realized in practice, and further studies are needed.  Importantly, Transpara AI is FDA cleared and CE-marked for use on 2D and tomosynthesis mammograms, but it was not stated if all mammograms in this analysis were 2D or how many were tomosynthesis.


1 Half the mammograms were performed on Hologic and half on Siemens. Median exam level breast density was higher for mammograms performed on Hologic equipment, at 7.8% (IQR 5.8-11.6) vs. 6.7% (IQR 5.4-9.4) for Siemens, and 3.3% were classified as VBD category 4 on Siemens vs. 6.7% on Hologic.

2 Comparing right and left breasts, 18.5% were classified into different VBD groups (20.2% for Siemens and 16.7% for Hologic).

3 AUC for VBD 1 was 0.955 and decreased with increasing density to 0.857 for VBD 4.  Differences between categories were significant except for VBD 3 vs. 4 (where P=.094).  Using area-based AI density, AUC was also significantly lower for heterogeneously dense vs. scattered density, for each vendor.  The percentage of screen-detected cancer with the highest AI risk score of 10 varied by breast density from 86.7% for VBD 1, 92.7% for VBD 2, 94.6% for VBD 3, to 93.3% for VBD 4.

Filed Under: Blog

Does Screening Automated Breast Ultrasound (ABUS) Reduce False Alarms Compared to Handheld US (HHUS) in Women with Dense Breasts?

August 13, 2026 by Dense Breast Info

Background

Supplemental US is commonly recommended for women with dense breasts who cannot undergo breast MRI or who need additional screening beyond mammography. Although annual HHUS improves cancer detection by an average of 2-3 cancers per 1000 women screened, it is highly operator dependent and frequently results in BI-RADS 3 assessments that require short-interval follow-up.

Automated breast ultrasound (ABUS) was developed to provide standardized whole-breast imaging with improved reproducibility. Until recently, however, relatively few large-scale U.S. analyses have compared the performance of ABUS with HHUS in routine clinical practice.

Recent Study

In a recent study using Breast Cancer Surveillance Consortium (BCSC) data, investigators evaluated 25,328 supplemental screening US examinations performed in 21,446 women with dense breasts between 2014 and 2020.¹ The examinations were interpreted by 98 radiologists across 27 U.S. imaging facilities. Researchers compared the performance of ABUS and HHUS after adjusting for patient breast cancer risk and facility characteristics.

Key Findings

  • ABUS was associated with a significantly lower abnormal interpretation and false-positive rates compared to HHUS.²
  • The rate of short-interval follow-up recommendations was substantially lower for ABUS than for HHUS.³
  • Cancer detection rates (CDR) were comparable between the two modalities⁴.
  • There were no significant differences in biopsy recommendation rates or actual biopsies performed between ABUS and HHUS⁵.

These findings suggest that ABUS is an effective alternative to HHUS for supplemental screening in women with dense breasts. With ABUS, it is easier to recognize multiplicity and bilaterality of benign-appearing masses and to assess such cases as BI-RADS 2, benign, rather than BI-RADS 3 with unnecessary six-month follow-up examinations, patient anxiety, and associated healthcare costs. Importantly, these improvements were achieved without compromising cancer detection, as ABUS detected cancers at rates comparable to HHUS while generating fewer false-positive screening assessments. By providing standardized, reproducible whole-breast imaging that is less dependent on operator technique, ABUS may improve the consistency and efficiency of supplemental screening programs for women with dense breasts.

Limitations

ABUS generates over 1000 images for review and interpretation time was not considered.  Unlike HHUS, there is no Doppler or elastography with ABUS, sometimes necessitating recall for more complete characterization of findings. False-positive rates decrease with incidence screening and this study did not distinguish prevalence from incidence screens, with 70.5% of the examinations reported having no prior screening US.  The BCSC registries may not fully represent all U.S. screening practices, and investigators could not determine whether HHUS examinations were performed by radiologists or technologists. Cancer outcomes were limited to 90-day follow-up, potentially underestimating cancers initially classified as BI-RADS 3. Incomplete one-year follow-up prevented formal estimates of sensitivity and specificity.

Detailed Results

¹ The study included 21,446 women with dense breasts who underwent 25,328 supplemental screening US examinations, including 4,218 ABUS and 21,110 HHUS examinations. Most examinations were performed in women with heterogeneously dense breasts (21,913; 87%), while 3,415 (13%) were performed in women with extremely dense breasts.  The vast majority of women had tomosynthesis (22,383; 89% overall).

² The adjusted abnormal interpretation rate was 14.9% (95% CI, 13.8%–15.9%) for ABUS compared with 19.2% (95% CI, 18.7%–19.8%) for HHUS (P<.0001). ⁶ Adjusted false-positive initial assessment rates were 14.6% (95% CI, 13.6%–15.7%) for ABUS compared with 19.1% (95% CI, 18.5%–19.6%) for HHUS (P<.0001).

³ The adjusted short-interval follow-up recommendation rate was 3.0% (95% CI, 2.5%–3.5%) for ABUS versus 14.6% (95% CI, 14.1%–15.0%) for HHUS (P<.0001).

⁴ Adjusted cancer detection rates were statistically similar between ABUS and HHUS at 2.5 cancers per 1,000 examinations (95% CI, 1.0–4.0) versus 1.7 cancers per 1,000 examinations (95% CI, 1.1–2.2), respectively (P=.33).

⁵ Adjusted biopsy rates were similar for ABUS (2.7%; 95% CI, 2.2%–3.2%) and HHUS (2.6%; 95% CI, 2.4%–2.8%) (P=.75) and PPV3 of biopsies remained low at 9.5% (95% CI 3.8%-15.3%) for ABUS and 6.4% (95% CI 4.3%-8.5%) for HHUS (P=.33).


Filed Under: Blog

Do Dense Breast Laws Increase Use of Supplemental Screening?

August 7, 2026 by Dense Breast Info

Background

Screening mammography remains the cornerstone of breast cancer screening, but cancers are often masked in women with dense breasts, increasing the risk of interval cancers and delaying diagnosis. Dense breasts also increase the risk of developing breast cancer (see how breast density compares to other risk factors).  Because of these challenges, supplemental screening breast MRI is recommended [or ultrasound (US) if MRI is not an option] for women with extremely dense breasts, women with heterogeneously dense breasts who have other risk factors, and for high-risk women with any breast density.

To improve patient awareness and access to supplemental screening, many U.S. states have enacted dense breast legislation. These laws typically fall into two categories: inform (also called “notification”), or insurance coverage. Inform mandates require radiologists to include information about breast density in the mammogram results letter, with a national standard mandated by the FDA as of 9/10/2024.  Insurance mandates require insurers to cover supplemental screening (though coinsurance and deductibles often apply and there are many exemptions), with a patchwork of state laws.  Federal HRSA guidelines effective 1/1/2026 have set a federal standard for expanded insurance coverage for most private plans, but Medicare, Tricare, and VHA are exempt, and Medicaid coverage varies.  The Find It Early Act would address gaps in coverage, and reaching out to senators and representatives in support of this act is important.

Recent Study

In this retrospective quasi-experimental cohort study using the USA national MarketScan Commercial Claims and Encounter Database from 2008 through 2019, researchers evaluated which legislative frameworks and specific messaging features were most effective at driving the clinical uptake of supplemental imaging. The study included 12,555,082 commercially insured women aged 40–64 years who underwent screening mammography and maintained continuous insurance coverage for at least six months afterward. Using a staggered-adoption difference-in-differences design, investigators evaluated how different state dense breast laws influenced the use of screening US and MRI.

Key Findings

  • Insurance coverage mandates were the strongest legislative driver of screening US use¹.
  • Dense breast inform mandates independently increased the use of both screening US and MRI².
  • Inform laws that explicitly mentioned the potential benefit of supplemental screening were associated with substantially greater US utilization³.
  • Targeted notifications directed specifically to women with dense breasts were more effective than universal notifications at increasing use of supplemental screening⁴.
  • Despite these legislative changes, the overall use of supplemental screening remained low across the study population⁵.

The findings suggest that insurance coverage is the most important factor in translating patient awareness into clinical action. While inform laws increased awareness, insurance mandates had a much greater impact on supplemental US use (13 vs. 47 additional examinations per 1,000 women), highlighting the importance of reducing financial barriers. Laws that notified only women with dense breasts and included information about supplemental screening were more effective than universal notification of all women. Although insurance coverage increased screening US use, MRI utilization remained low, suggesting that factors beyond insurance, such as access, availability, referral patterns, and patient preference, continue to limit its use.

Limitations

Claims data could not reliably distinguish screening from diagnostic imaging, which may have overestimated supplemental screening rates. The study included only commercially insured women, and do not generalize to Medicare, VHA, Tricare, Medicaid, or uninsured populations.  Claims data lacked patient level characteristics, including breast density: uptake rates were determined across all women and are expected to be substantially higher in women with dense breasts. The authors did not distinguish state laws that require informing all woman of their specific density category (e.g. PA) vs. those that sent general information to all women about breast density (e.g. CT). These data preceded the 2024 national FDA standard. Further studies integrating claims data with cancer registries and electronic health records are needed to determine whether current legislative changes ultimately improve breast cancer outcomes.

Detailed Results

¹ Insurance coverage mandates increased supplemental US use by an absolute 4.7 percentage points (47 additional examinations per 1,000 women) and this represented significantly higher odds of US utilization (OR, 1.88; 95% CI, 1.86–1.90). MRI insurance coverage was not associated with increased MRI use (OR, 1.01; 95% CI, 0.96–1.05).

² Notification mandates were associated with modest but significant increases in use of screening US (OR, 1.09; 95% CI, 1.08–1.10) and breast MRI (OR, 1.09; 95% CI, 1.06–1.12). These findings corresponded to approximately 13 additional screening US examinations and 1 additional screening MRI examination per 1,000 women.

³ Notifications that included explicit language about supplemental screening tests were associated with substantially greater US use (OR, 2.84; 95% CI, 2.81–2.86).

⁴ Targeted notifications (sent only to women with dense breasts) were associated with higher odds of use of screening US (OR, 1.32; 95% CI, 1.31–1.33) and breast MRI (OR, 1.23; 95% CI, 1.19–1.27) compared with universal notification laws.

⁵ Across the entire study population of 12,555,082 women, only 9.0% underwent supplemental US and 0.6% underwent breast MRI within six months of screening mammography, demonstrating that overall supplemental screening remained relatively uncommon despite legislative changes. The study could not detail results by patient breast density or risk factors and was conducted at the state population level. The authors did report that 0.5% of the population had a personal history of breast cancer.

Filed Under: Blog

NEW! Mammography AI Screening Tools

July 31, 2026 by Dense Breast Info

Artificial intelligence (AI) is rapidly transforming breast imaging—from helping detect cancers on mammograms to improving workflow efficiency and identifying women who may benefit from supplemental screening based on their individual risk.

As interest in these technologies continues to grow, so do questions from both patients and healthcare providers. To help separate fact from hype, our DenseBreast-info.org experts have developed a comprehensive new resource, Mammography AI Screening Tools, that explains the current role of AI in breast imaging in clear, practical terms.

The resource answers common questions, reviews how AI is being used today, explores its potential and limitations, and includes easy-to-reference tables designed to help breast imaging professionals better understand the available tools and their clinical applications.

True to our mission, we are delighted to share this new educational tool.

Filed Under: Blog

What Are the Outcomes from Continued Screening Contrast-Enhanced Mammography?

July 30, 2026 by Dense Breast Info

Standard mammography reduces breast cancer mortality but is less sensitive in women with dense breasts. Contrast-enhanced mammography (CEM) combines mammography with intravenous iodinated contrast. CEM thereby depicts tumor-associated blood flow and provides functional information similar to breast MRI.

Most studies have evaluated CEM during an initial (prevalence) screening examination and have shown very promising results. Less is known about its performance during subsequent (incidence) screening rounds. In a recent retrospective study from Memorial Sloan Kettering Cancer Center, investigators evaluated CEM examinations performed between 2015 and 2021. Most women were at increased risk for breast cancer and had dense breast tissue1. The authors compared cancer detection rate, sensitivity, specificity, and cancer characteristics from first screens vs. those with a prior comparison CEM or MRI.

Key Findings

  • CEM maintained high sensitivity and cancer detection rates during both prevalence and incidence screening rounds.²
  • Specificity and overall accuracy improved significantly during incidence screening compared with the initial examination.³
  • More than half of cancers were seen only because of contrast enhancement.⁴
  • CEM continued to detect predominantly invasive, node-negative cancers during subsequent screening rounds.5

These findings suggest that CEM remains an effective supplemental screening tool over repeated examinations. The improved specificity seen during incidence screening may reduce unnecessary recalls while maintaining high cancer detection.

There were limitations to this study. It was a retrospective, single-center analysis involving primarily women with a personal history of breast cancer, which may limit generalizability. Larger prospective studies, including the ongoing CMIST trial, are needed to further define the role of CEM in risk-based screening. CEM is currently only FDA approved for diagnostic use, not screening.  Contrast-enhanced biopsy capability is necessary for centers performing CEM.  In this study, biopsies were performed using MRI guidance, but not all women having CEM can tolerate MRI: direct CEM-guided biopsy should be available.

In an accompanying editorial, Freitas et al. noted that these findings support CEM as a practical screening option, particularly for women who cannot undergo breast MRI or in settings where MRI access is limited.  Because low-energy images mimic standard mammography, CEM can be performed instead of standard mammography rather than as a supplement.

Detailed Results

¹ Most women had dense breast tissue. Dense breasts (BI-RADS C or D) were present in 83.1% of women undergoing prevalence screening and 88.2% of women undergoing incidence screening.  Of 1575 prevalence screens, 941 (59.7%) were in women with a personal history of breast cancer, as were 2894/5336 (54.2%) of incidence screens.

² Sensitivity remained stable at 86.1% (30/35) during prevalence screening and 87.1% (62/71) during incidence screening (P=.60). Cancer detection rates (CDR) were 19.0 per 1,000 examinations during prevalence screening and 11.6 per 1,000 examinations during incidence screening (P=.65). 

³ Specificity increased from 83.4% (95% CI, 81.6–85.4%) during prevalence screening to 91.5% (95% CI, 90.7–92.2%) during incidence screening (P=.008). Overall accuracy increased from 83.5% to 91.4% (P=.01).

⁴ Contrast enhancement alone showed 60% (18/30) of cancers during prevalence screening and 58% (36/62) during incidence screening.  Incremental CDR due to contrast was 11.4/1000 for prevalence screening and 6.7/1000 for incidence screening.

5 There was no significant difference in tumor subtype between screening rounds (P=.50). Most cancers were invasive (70.0% during prevalence screening and 61.2% during incidence screening), and lymph node positivity remained low (5.9% vs. 6.1%). Mean invasive tumor size was 8 mm (range 6-11 mm) for prevalence screens and 7 mm (range 4-10 mm) for incidence screens. The interval cancer rate was 5/1292 (3.9/1000) for prevalence screens and 9/4828 (1.9%) for incidence screens.

Filed Under: Blog

  • Page 1
  • Page 2
  • Page 3
  • Interim pages omitted …
  • Page 22
  • Go to Next Page »

Primary Sidebar

DenseBreast‑info, Inc. is an independent, nonprofit organization. DBI is not affiliated with or endorsed by other organizations unless expressly identified. If you have questions about DBI’s programs or partnerships, please contact us.

© Unpublished, DenseBreast-info, Inc. ALL RIGHTS RESERVED | 501(c)(3) Public Charity

  • Online Privacy Policy
  • Online Terms of Use & Disclaimers

This website is for informational purposes only and is not intended to be a substitute for medical advice from a physician or to create a standard of care for health care providers. In addition, information has been provided by independent third parties and may not represent the views of DenseBreast-info.org. Please check with a physician regarding your specific condition, if you have any questions, or need a diagnosis. If you are experiencing an urgent medical condition, call your local emergency services [e.g., 9-1-1 (in the USA) or 1-1-2 (in Europe)].